Pediatric Venous Thrombosis Associated With Staphylococcal Infections: A Single Institutional Experience

Pediatric Venous Thrombosis Associated With Staphylococcal Infections: A Single Institutional Experience

Year: 2015
Grants:
Bleeding Disorders Conference
Clinical Research/Clinical Trials
Author(s):
Divyaswathi Citla Sridhar, Ossama M. Maher, Fernando Corrales-Medina, Hatel Rana Moonat, Jorge Galvez Silva, Trinh Nguyen, Deborah Brown, Nidra I. Rodriguez

Introduction:

Since the emergence of community-acquired methicillin-resistant S. aureus (MRSA), severe manifestations of infection are encountered more frequently. Venous thrombosis (VT) has been previously reported in children with S. aureus infections. This study reviews our institutional experience and outcomes of children with VT and staphylococcal infections.

Methods:

A retrospective analysis of 15 pediatric patients (≤ 18 years) treated for VT and staphylococcal infections at Children’s Memorial Hermann Hospital between January 1, 2010 and December 31, 2014 was performed.

Results:

Fifteen patients were included (10 males, 5 females) with a median age at diagnosis of 8 years (range 2 mo-17yrs). Underlying infections included: osteomyelitis (n=7), soft tissue infection (n=3), aortitis (n=1), meningitis (n=1), septic arthritis (n=1), central line infection (n=1), septicemia (n=1). Primary presentation included: swelling (n=12), pain (n=11), tenderness (n= 8), and color changes (n=3). One patient had prior history of VT. Family history was positive for VT in one patient. Isolated organisms included: MRSA (n=9), MSSA (n=3), polymicrobial (n=2), and Staphylococcus non- aureus (n=1). Eight patients had central venous catheters (CVC) and 5 of them had thrombosis at the CVC site. VT sites identified by Doppler US (DUS) included: upper extremity (n= 5), lower extremity (n= 8), and neck (n=2). All thrombophilia work up was negative. The median D-dimer at diagnosis was 3 ug/ml (range: 0.31- 6.54 ug/ml). Median time elapsed between infection and VT diagnosis was 5.5 days (range: 0-35 days). All patients received anticoagulation using LMWH (1mg/kg/dose) except one who had superficial thrombophlebitis and was managed conservatively. Median time to achieve therapeutic anti- factor Xa level was 2.5 days (range 1- 6 days). Median duration of anticoagulation was 3 months. Three out of 13 patients (23%) had resolution of thrombosis within one week of anticoagulation. Four other patients had thrombus resolution by DUS at 3-6 months. Five patients did not have DUS at 3-6 months. None of the 15 patients required hospital re- admission for bleeding or thrombotic complications.

Discussion:

Staphylococcal infections may increase the risk of VT in children. Nine out of 15 patients (60%) with VT had a documented MRSA infection, which appears to confer an even higher risk for development of VT. Over half of the patients responded favorably to anticoagulation with resolution of VT within 6 months.

Conclusions:

A high index of suspicion for VT is warranted in children with Staphyloccoccal infections (particularly MRSA) to promptly diagnose and treat. This approach may improve outcomes and minimize complications including septic emboli and post-thrombotic syndrome. Prophylactic anticoagulation in presence of MRSA infection could be considered in future studies.

Keywords: Children, staphylococcal infection, venous thrombosis

Description and Management of Pain and Functional Impairment in US Adults With Hemophilia: Initial Observations From the Pain, Functional Impairment, and Quality of Life (P-FiQ) Study

Description and Management of Pain and Functional Impairment in US Adults With Hemophilia: Initial Observations From the Pain, Functional Impairment, and Quality of Life (P-FiQ) Study

Year: 2015
Grants:
Bleeding Disorders Conference
Quality of Life/Outcomes Research
Author(s):
Michelle Witkop, Kim Baumann, Tyler Buckner, Stacie Akins, Sharon Funk, Grace Hernandez, Michael Recht, Michael Wang, Katharine Batt, Christine Kempton, David Cooper

Objective:

Hemophilia is marked by frequent joint bleeding, resulting in acute and chronic pain and functional impairment. Surveys in US adults with hemophilia demonstrate suboptimal pain management and quality of life (QoL). The objective of P-FiQ was to methodologically assess QoL parameters, including functional impairment and pain, and pain management strategies.

Methods:

Adult men with mild-severe hemophilia with a history of joint pain and/or bleeding completed a hemophilia/pain history and various patient-reported outcome assessments (completed twice in “retest” population of initially enrolled patients).

Summary:

Of 164 adults with hemophilia (median age 34) in the “retest” population, more had hemophilia A (74%) than B (26%); 6% had inhibitors. Most had some college-or-above education (63%), 81% were employed, 61% were overweight/obese, and 61% self-reported arthritis/bone/joint problems. Current patient-reported treatment regimens were prophylaxis (42%), on-demand (39%), or mostly on-demand (19%; 25/31 using infusions ahead of activity). One-third (32.9%) reported unrestricted school/work/recreational activities in the prior 6 months; 6.2% reported needing assistance for school/work/self-care, or did not participate in recreational activities because of pain, loss of motion, and weakness. Some patients (31.3%) reported using a cane/crutches/walker (3.8% always) and 7.6% a wheelchair (1.3% always), and 47.0% reported a history of joint surgery (41 knee, 37 ankle, 29 elbow). Patients reported losing an average of 3.7 and 1.8 school/work days in the previous 6 months due to lower and upper extremity problems, respectively. Patients reported that during the prior 6 months they had experienced acute pain only (24%), chronic pain only (33%), or both (29%); 15% reported no pain. Acute pain was most frequently described as sharp (77%), aching (66%), shooting (57%), and throbbing (55%), and chronic pain as aching (74%), nagging (49%), throbbing (44%), and sharp (40%). Most common analgesics in the past 6 months for acute/chronic pain were acetaminophen (69%/58%), NSAIDs (40%/52%), hydrocodone-acetaminophen (29%/33%), oxycodone (12%/11%), and oxycodone- acetaminophen (9%/8%). Most common nonanalgesic treatment strategies reported for acute/chronic pain in the past 6 months were ice (73%/37%), rest (48%/34%), factor or bypassing agent (48%/24%), elevation (34%/28%), relaxation (31%/23%), compression (27%/21%), and heat (25%/15%); other reported strategies include medical marijuana (17%/9%), physical therapy (12%/9%), prayer (11%/8%), faith (9%/8%), alcohol (8%/7%), aquatherapy (5%/6%), illicit drugs (4%/2%), acupuncture (2%/1%), hypnosis (2%/1%), and biofeedback (1%/1%).

Conclusions:

Initial data corroborate the high prevalence of pain and functional disability in adults with hemophilia and highlight opportunities to address clinical assessment, patient dialogue, and management strategies to improve outcomes.

Long-term safety and efficacy of recombinant factor IX Fc (rFIXFc) in adults and adolescents with severe hemophilia B: interim results of the B-YOND study

Long-term safety and efficacy of recombinant factor IX Fc (rFIXFc) in adults and adolescents with severe hemophilia B: interim results of the B-YOND study

Year: 2015
Grants:
Bleeding Disorders Conference
Clinical Research/Clinical Trials
Author(s):
Amy D Shapiro, John Pasi, Margaret Ragni, Johnny Mahlangu, Margareth Ozelo, Johannes Oldenburg, Tadashi Matsushita, Ross I Baker, Huixing Yuan, Alejandra Ramirez-Santiago, Glenn F Pierce, Geoffrey Allen, Baisong Mei

Objective:

The ongoing rFIXFc extension study, B-YOND (clinicaltrials.gov #NCT01425723), evaluates the long-term safety and efficacy of rFIXFc for the treatment of severe hemophilia B. Here we report interim safety and efficacy data for adults and adolescents enrolled in B- YOND.

Methods:

Upon completing B-LONG, eligible subjects could enroll in one of 4 treatment groups in B-YOND: weekly prophylaxis (20 to 100 IU/kg every 7 days), individualized prophylaxis (100 IU/kg every 8 to 16 days, or twice monthly), modified prophylaxis (a prophylaxis regimen different from weekly or individualized prophylaxis), or episodic treatment. Subjects could change treatment groups at any point in the study. The primary endpoint was development of inhibitors. Secondary outcomes included annualized bleeding rate (ABR) and rFIXFc exposure days (EDs).

Summary:

93/115 subjects (80.9%) who completed B-LONG enrolled in B-YOND. As of the interim data cut (17 October 2014), 18 subjects had completed, 7 had discontinued, and 68 remained on study (median time on study, 119.9 weeks). From the start of B-LONG to the B- YOND interim data cut, the median time on rFIXFc was 171.6 weeks and 68 subjects (73%) had ≥100 cumulative rFIXFc EDs. 29/90 subjects (32%) from Arms 1-3 of B-LONG changed treatment groups at the start of or during B-YOND, including 9/19 subjects who changed from episodic to prophylactic treatment (1 subject changed back to episodic treatment before the interim data cut). In the weekly prophylaxis group, the median (IQR) average weekly prophylactic dose was 49.5 (21.0, 105.6) IU/kg. The median (IQR) average dosing intervals in the individualized and modified prophylaxis groups were 13.7 (10.1, 14.0) days and 6.9 (4.9, 7.0) days, respectively (a reduction in annual infusions of ~75% and ~50%, respectively, compared with twice-weekly administration of a standard half-life FIX product). As of the B- YOND interim data cut, no inhibitors were observed, and there were no reports of anaphylaxis or serious hypersensitivity reactions associated with rFIXFc, and no thrombotic events. Adverse events were generally typical of the hemophilia B population; no subject discontinued due to an adverse event. Median ABRs were low with rFIXFc prophylaxis (Table). 97.2% of bleeding episodes were controlled with 1 or 2 infusions.

Conclusions:

Interim data from B- YOND confirm the long-term safety of rFIXFc and the maintenance of a low ABR with prophylactic dosing every 1 to 2 weeks.

Low Annualized Bleeding Rates in Phase 3 Studies of Recombinant Factor VIII Fc Fusion Protein (rFVIIIFc) in Subjects with Target Joints at Baseline

Low Annualized Bleeding Rates in Phase 3 Studies of Recombinant Factor VIII Fc Fusion Protein (rFVIIIFc) in Subjects with Target Joints at Baseline

Year: 2015
Grants:
Bleeding Disorders Conference
Clinical Research/Clinical Trials
Author(s):
Michael Wang, Beatrice Nolan, Guy Young, Savita Rangarajan, Bryce Kerlin, Roshni Kulkarni, Margaret V. Ragni, Ross I. Baker, Elisa Tsao, Desilu Glazebrook, Glenn Pierce, Geoffrey Allen

Introduction and Objectives:

The phase 3 A-LONG and Kids A-LONG studies demonstrated the safety and efficacy of rFVIIIFc for the control and prevention of bleeding episodes in subjects with severe hemophilia A. This subgroup analysis of A-LONG and Kids A-LONG examined bleeding frequency with rFVIIIFc prophylaxis in subjects with target joints at baseline.

Methods:

A-LONG (≥12 y) and Kids A-LONG (<12 y) subjects with a history of target joints (a major joint with ≥3 bleeding episodes in a 6-month period) who were previously treated with FVIII and received on-study rFVIIIFc prophylaxis were identified. Self-reported pre-study 12- month bleeding history and on-study annualized bleeding rate (ABR) for all bleeds were evaluated.

Results:

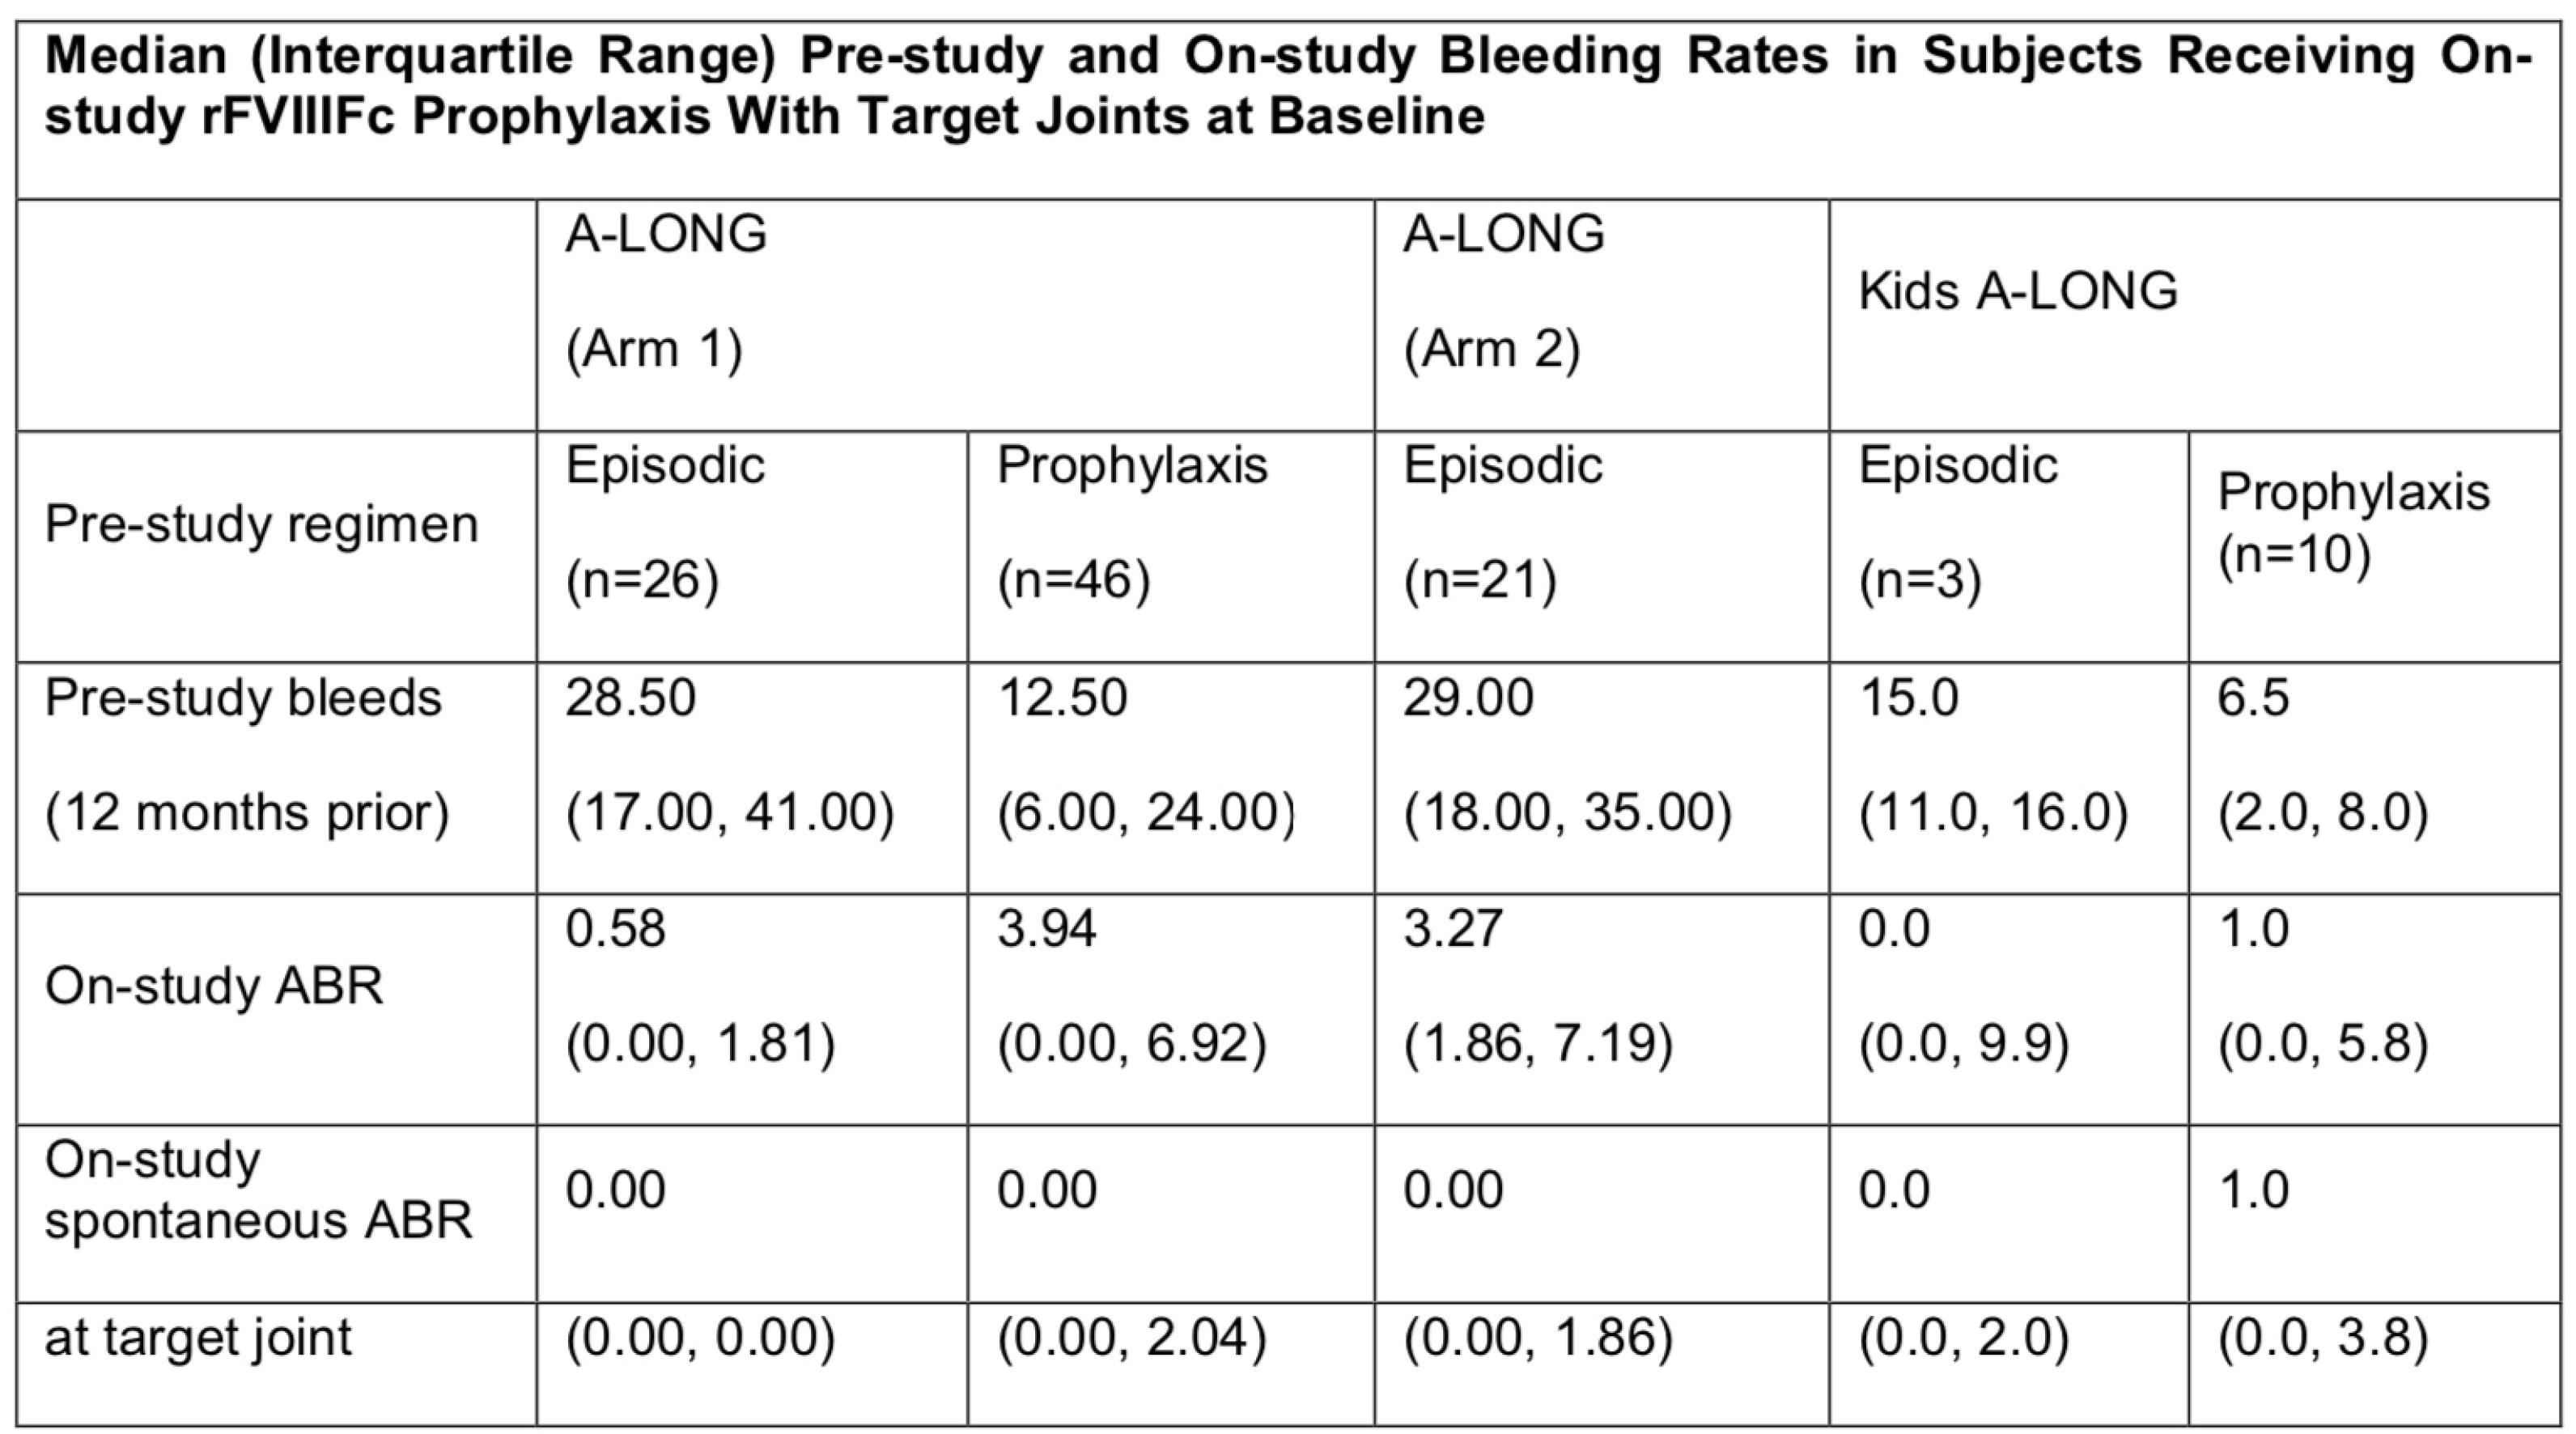
93/141 subjects in A-LONG and 13/69 subjects in Kids A-LONG had target joints at baseline. The most prevalent locations of pre-study target joints identified at baseline among subjects in A-LONG were the elbow (61.7%) and ankle (59.6%). Similarly, in Kids A-LONG, these were the ankle (69.2%) and elbow (30.8%). A total of 59.7% and 52.4% of subjects receiving individualized (Arm 1) and weekly (Arm 2) rFVIIIFc prophylaxis in A-LONG, respectively, and 53.8% of subjects receiving rFVIIIFc prophylaxis in Kids A-LONG with target joints at baseline had no target joint bleeding episodes on-study. Median on-study ABRs with rFVIIIFc prophylaxis tended to be lower than pre-study bleeding rates in subjects with target joints at baseline (Table).

Conclusions:

For subjects with severe hemophilia A who had target joints at baseline, rFVIIIFc prophylaxis lowered bleeding rates across age groups compared with pre-study FVIII treatment.

Table. Median (Interquartile Range) Pre-study and On-study Bleeding Rates in Subjects Receiving On- study rFVIIIFc Prophylaxis With Target Joints at Baseline


BAY 81-8973: The Effects of Routine Prophylaxis on Total, Joint, and Spontaneous Bleeding in Adolescents, Adults, and Children With Severe Hemophilia A

BAY 81-8973: The Effects of Routine Prophylaxis on Total, Joint, and Spontaneous Bleeding in Adolescents, Adults, and Children With Severe Hemophilia A

Year: 2015
Grants:
Bleeding Disorders Conference
New Products
Author(s):
Sanjay Ahuja, Bryce Kerlin, Thomas J Humphries, Olubunmi Afonja, Monika Maas Enriquez

Introduction:

BAY 81-8973 is Bayer’s new full-length recombinant factor VIII (FVIII) product for the treatment of hemophilia A, with no human- or animal-derived raw materials added to the cell culture, purification, or formulation process.

Methods:

The safety and efficacy of BAY 81-8973 for routine prophylaxis in patients with severe hemophilia A (<1% FVIII) was evaluated in 3 clinical studies: 2 in adolescent and adult previously treated patients (PTPs; aged 12–65 years [Study 1 and Study 2]) and 1 in children aged ≤12 years (PTPs: completed [Study 3]; previously untreated patients: ongoing), enrolling a total of 204 patients. In Study 1, the prophylaxis regimen was 20–50 IU/kg 2x–3x/wk as determined by the investigator. In Study 2, patients were randomized to prophylaxis (20–30 IU/kg 2x/wk or 30–40 IU/kg 3x/wk) or on-demand treatment. In both 12-month studies, the primary efficacy variable was the annualized bleeding rate (ABR). In Study 3, the prophylaxis regimen was 20–50 IU/kg 2x–3x/wk or every other day, as determined by the investigator, for ≥50 exposure days (approximately 6–8 months). The primary efficacy variable was the ABR for total bleeds occurring within 48 hours of previous prophylaxis treatment; ABR was also analyzed independent of time of injection.

Results:

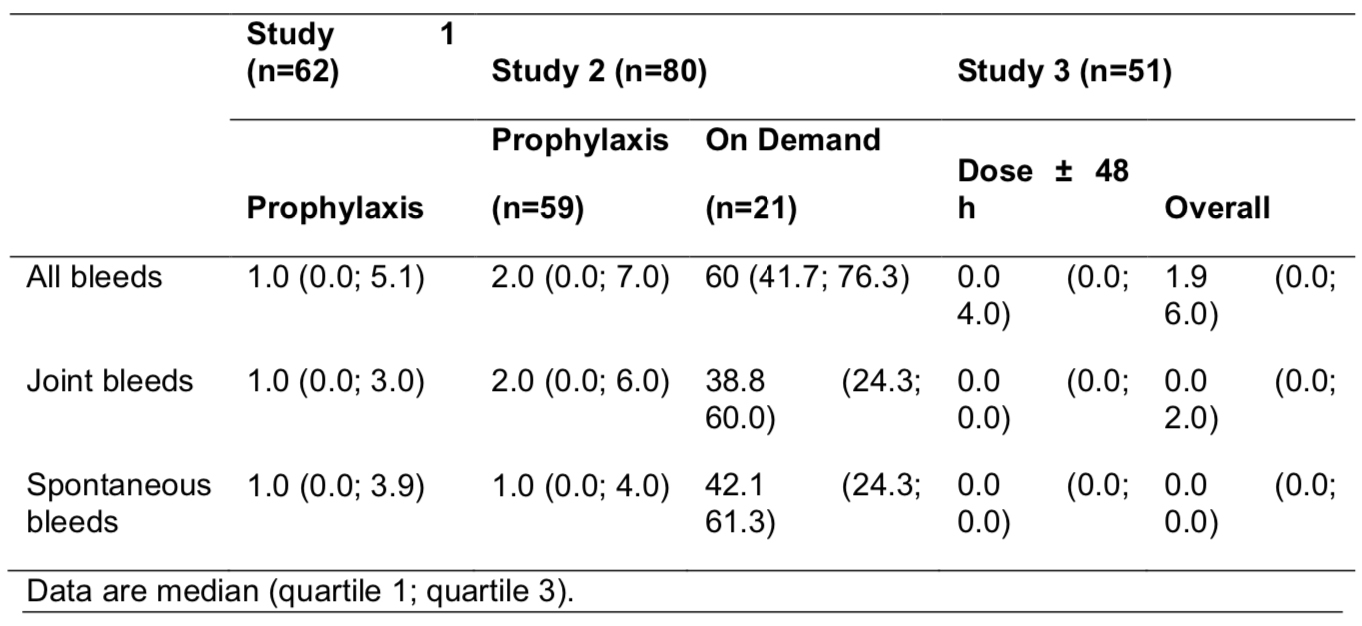
A total of 193 patients treated with BAY 81-8973 were included in the analysis (Table 1). Sixteen (25.8%), 16 (27.1%), and 23 (45.1%) patients treated prophylactically had 0 bleeding episodes in Studies 1, 2, and 3, respectively.

Table 1. Annualized Bleeding Rates

Table 1. Annualized Bleeding Rates

Conclusions:

Study 1 and Study 2 demonstrated the efficacy and safety of routine prophylaxis treatment with BAY 81-8973 in adolescents and adults. Study 2 also demonstrated the superiority of prophylaxis over on-demand treatment during a one-year treatment period. An additional study in children aged ≤12 years showed low annualized rates for all bleeds, joint bleeds, and spontaneous bleeds within 48 hours after injection or later during routine prophylaxis.

NHF Avatar

Understanding the Interplay between Electron Transfer and VKOR Supported Blood Coagulation

Year:
-
Grants:
Nicholas Cirelli Family
Judith Graham Pool Postdoctoral Research Fellowship
Vitamin K
Author(s):
Wei Cheng
BAY 81-8973: Safety Observations in Clinical Trials in Adults, Adolescents, and Children With Severe Hemophilia A

BAY 81-8973: Safety Observations in Clinical Trials in Adults, Adolescents, and Children With Severe Hemophilia A

Year: 2015
Grants:
Bleeding Disorders Conference
New Products
Author(s):
Miguel Escobar, Dana Obzut, Thomas J Humphries, Olubunmi Afonja, Elke Detering

Introduction:

BAY 81-8973 is Bayer’s new full-length recombinant factor VIII (FVIII) product in development for the treatment of hemophilia A. BAY 81-8973 has no human- or animal- derived raw materials added to the cell culture, purification, or formulation processes.

Objective:

To evaluate the safety profile of BAY 81-8973 as documented in clinical trials with BAY 81-8973.

Methods:

The safety of BAY 81-8973 for prevention and treatment of bleeds in patients with severe hemophilia A (<1% FVIII) was evaluated in 3 clinical studies: 2 in adolescent and adult previously treated patients (PTPs; aged 12–65 years with ≥150 previous exposure days [EDs]) and 1 in pediatric PTPs (aged ≤12 years with ≥50 previous EDs). A total of 193 PTPs (including 51 pediatric patients) were included to assess the frequency of adverse reactions in the 3 phase 3 studies. The immunogenicity of BAY 81-8973 was also evaluated in PTPs. Adverse reactions were collected and analyzed throughout the studies.

Results:

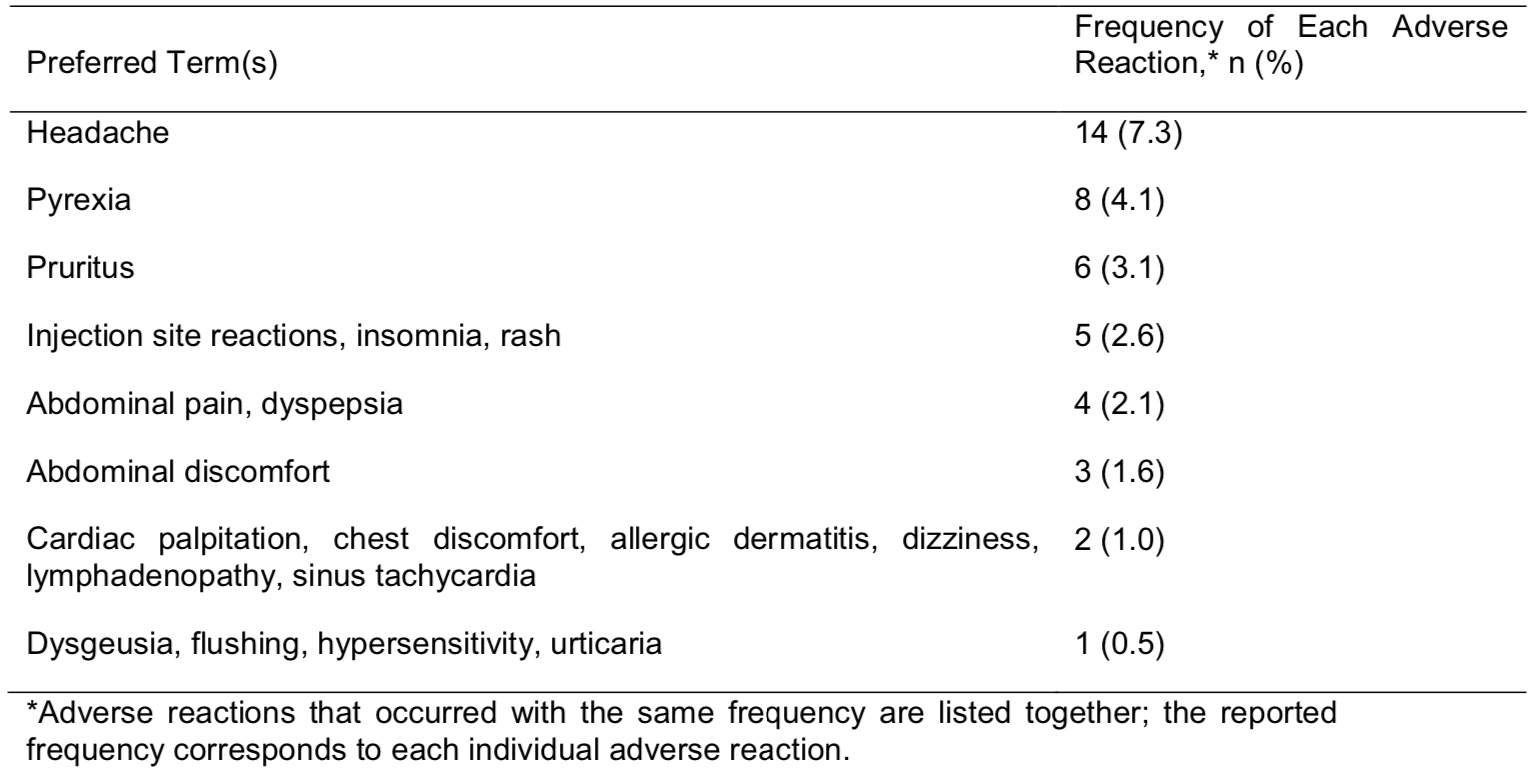
The frequency, type, and severity of adverse reactions in children were similar to those in adults. Adverse reactions in PTPs are listed in Table 1. In PTPs evaluated to date for immunogenicity, no inhibitors were detected.

Table 1. Adverse Reactions in Previously Treated Patients (N=193)

Table 1. Adverse Reactions in Previously Treated Patients (N=193)

Conclusions:

The incidence of treatment-related adverse and serious adverse reactions in the BAY 81-8973 trials was low (<10%) and similar to those reported in the literature for other full-length FVIII products. No PTP developed a FVIII inhibitor.

Patients Treated with Recombinant Factor VIII Fc Fusion Protein (rFVIIIFc) Reported Increased or Maintained Physical Activity in the A-LONG and Kids A-LONG Studies

Patients Treated with Recombinant Factor VIII Fc Fusion Protein (rFVIIIFc) Reported Increased or Maintained Physical Activity in the A-LONG and Kids A-LONG Studies

Year: 2015
Grants:
Bleeding Disorders Conference
Clinical Research/Clinical Trials
Author(s):
Doris Quon, Robert Klamroth, Roshni Kulkarni, Amy Shapiro, Ross Baker, Giancarlo Castaman, Bryce Kerlin, Elisa Tsao, Geoffrey Allen

Introduction and Objectives:

In the phase 3 A-LONG and Kids A-LONG studies, subjects with severe hemophilia A receiving rFVIIIFc prophylaxis 1-2 times/week had low annualized bleeding rates (ABRs), with comparable pre-study and on-study weekly factor consumption for subjects previously on FVIII prophylaxis. This report evaluated the effect of rFVIIIFc on subjects’ physical activity across a variety of age groups using a subject-reported assessment.

Methods:

Subjects eligible for A-LONG (≥12 y) and Kids A-LONG (<12 y) were previously treated males with severe hemophilia A (<1 IU/dL endogenous FVIII activity). Subjects in A- LONG were enrolled into 1 of 3 arms: Arm 1, individualized prophylaxis; Arm 2, weekly prophylaxis; or Arm 3, episodic treatment. All subjects in Kids A-LONG received rFVIIIFc prophylaxis. There were no restrictions regarding physical activity. Physical activity assessments were conducted at Weeks 7, 14, 28, 38, 52, and end of study (A-LONG) and Weeks 2, 7, 12, 17, 22, 26, and end of study (Kids A-LONG). At each visit after their first rFVIIIFc dose, subjects were asked to report any changes in their activity levels relative to their prior study visit as: more (or more intensive), fewer (or less intensive), or about the same amount of physical activities. To summarize each subject’s change in physical activity during the study compared to baseline, subjects’ reports were classified into four groups: less, the same, more, or undetermined.

Results:

A total of 165 and 71 subjects enrolled in A-LONG and Kids A-LONG, respectively. Overall, the majority of subjects in A-LONG reported more or the same amount of physical activity, and few subjects reported less physical activity during the study (less, the same, more, undetermined in Arm 1 [n=117], 8%, 36%, 51%, 5%; Arm 2 [n=23], 9%, 48%, 39%, 4%; Arm 3 [n=23], 9%, 52%, 26%, 13%, respectively). Results were generally similar for subjects in Kids A-LONG (for subjects aged <6 y [n=35], 3%, 26%, 66%, 6%; for subjects aged 6 to <12 y [n=34], 9%, 26%, 56%, 9%).

Conclusions:

The majority of subjects in A-LONG and Kids A-LONG reported similar or increased physical activity levels during the studies, while maintaining low ABRs. These self- reported data suggest that subjects across a variety of age groups with severe hemophilia A who are transitioning to rFVIIIFc may maintain or increase physical activity levels, while reducing infusion frequency and maintaining similar weekly factor consumption, without compromising efficacy.

Increased physical activity levels and improvement in treatment outcomes in patients who switch from on-demand to prophylaxis with BAX 855

Increased physical activity levels and improvement in treatment outcomes in patients who switch from on-demand to prophylaxis with BAX 855

Year: 2015
Grants:
Bleeding Disorders Conference
New Products
Author(s):
Barbara A Konkle, Elizabeth L Schwartz, Josh Epstein, Andrea Hafeman, Leonard A. Valentino, Brigitt E. Abbuehl
HEMO-milestones tool increases assessment of self-management competency and plan for skill building in patients with hemophilia

HEMO-milestones tool increases assessment of self-management competency and plan for skill building in patients with hemophilia

Year: 2015
Grants:
Bleeding Disorders Conference
Psychosocial Issues
Author(s):
Maura Padula, Stacy Croteau, Ellis Neufeld, Loren D'Angelo, Kate Quint

Attainment of self-management skills, disease knowledge, and a documented transition plan are key elements for smooth transfer from pediatric to adult care for patients with chronic disease. Our hemophilia center had no standardized approach for assessing key patient competencies or independence readiness. In the last quarter of 2014, our team undertook a quality improvement project; we developed a transition tool with the goals of consistently assessing self-efficacy skills at a sustained rate of 90% during annual comprehensive visits; and developing patient-centric skill-building plans based on these assessments.

We previously reported that after four PDSA ramps of tool utilization, 31 patients, age 2-21 years, had been seen in hemophilia comprehensive clinic during the 3 month period studied. Utilizing the newly developed tool, 97% had a global assessment of competency with respect to their current age group; 93% had transition or progress plans documented. This demonstrated significant improvement compared with retrospective data from the three month period prior to implementation of the tool.

Since this previous report, we have continued to utilize the tool during hemophilia comprehensive clinic. In the proposed poster, we will demonstrate sustainability of the tool through analysis and presentation of Hemo-milestone data from the first half of 2015. Further, based on these results we will propose additional areas of study inspired by the transition tool, with the aim of continued improvement of the skill-building and transition process. These include improved utilization of educational materials based on identified learning needs; evaluation of documented, planned interventions; the development of collaborative educational events with our partner adult HTC; and retrospective, patient- centered evaluation of the transition process after the transition to adult hemophilia care.

Recombinant von Willebrand factor in severe von Willebrand disease: a prospective clinical trial

Recombinant von Willebrand factor in severe von Willebrand disease: a prospective clinical trial

Year: 2015
Grants:
Bleeding Disorders Conference
Clinical Research/Clinical Trials
Author(s):
Joan C. Gill, Giancarlo Castaman, Jerzy Windyga, Peter Kouides, Margaret Ragni, Frank W.G. Leebeek, Ortrun Obermann-Slupetzky, Miranda Chapman, Sandor Fritsch, Borislava G. Pavlova, Isabella Presch, Bruce Ewenstein

Objectives:

This trial evaluated the hemostatic efficacy, pharmacokinetics, and safety of a recombinant VWF (rVWF) in adults with severe von Willebrand disease (VWD) (type 3 [VWF:Ag ≤ 3 IU/dL], severe type 1 [VWF:RCo< 20 IU/dL], 2A [VWF:RCo< 20 IU/dL], 2N [FVIII:C<10% ], 2B, or 2M).

Methods:

Bleeds were to be treated initially with rVWF and rFVIII (1.3:1 ratio), followed by rVWF alone (as long as FVIII:C >40%). Hemostatic efficacy was evaluated using a pre- defined 4-point rating scale (none=4, moderate=3, good=2, excellent=1). PK parameters for rVWF vs. rVWF:rFVIII were assessed in a randomized crossover design, and a 6-month repeated PK evaluation for rVWF alone.

Summary:

Of 31 subjects assigned to bleed treatment, 22 (17 type 3, 4 type 2A and 1 type 2N) experienced 192 bleeding episodes (several in multiple locations) that were treated with rVWF: 106 occurred in mucosal tissue (including 32 menorrhagic, 42 nasopharyngeal, 26 mouth/oral bleeds), 59 joint bleeds, 6 gastrointestinal bleeds, and 37 in other locations. Treatment success (mean efficacy rating <2.5) was achieved in all 22 subjects (100%; Clopper-Pearson exact 90% confidence interval: 87.3 to 100.0). ‘Excellent’ ratings were given for 186/192 (96.9%) bleeds (119/122 minor, 59/61 moderate, 6/7 severe, 2/2 unknown severity) and the remaining 3.1% were ‘good’. One infusion was effective in 81.8% of bleeds (median [range]: 1 [1-4] overall; 2 [1-3] for severe bleeds). The subject’s own assessment of treatment efficacy (an exploratory endpoint), was ‘excellent’ within 8 hours after the first infusion for 125/134 (93.3%), ‘good’ for 8/134 (6.0%) and ‘moderate’ for 1/134 (0.7%) bleeding episodes. A substantial increase in FVIII:C and sustained stabilization (> 40% by 6 hours, rising to >80% 24 hours post-infusion) was observed after infusion with rVWF. PK parameters for VWF Ristocetin cofactor (VWF:RCo, a surrogate for the platelet-dependent function of rVWF) were similar when rVWF was infused alone (mean T1/2 21.9 h vs. 19.6 h with rVWF:rFVIII). Eight adverse events (tachycardia, infusion site paraesthesia, ECG t wave inversion, dysgeusia, generalized pruritis, hot flush, chest discomfort and increased heart rate) in 5 subjects were assessed as related to rVWF. No inhibitor or anti-VWF binding antibody development was observed, and there were no thrombotic events or severe allergic reactions.

Conclusions:

rVWF was safe, well-tolerated and effective in the treatment of a variety of bleeding presentations in severe VWD. The sustained stabilization in FVIII:C after the initial infusion enables subsequent infusion of rVWF without rFVIII, when multiple infusions are required.