Background:
Octanate is a highly purified, double virus inactivated, human plasma-derived factor VIII (FVIII) concentrate with all coagulation FVIII bound to its natural stabilizer VWF in a VWF:RCo/FVIII:C ratio of approximately 0.4. Five prospective GCP studies with octanate were conducted in 77 previously treated patients (PTPs) with severe haemophilia A. None of these 77 PTPs developed an inhibitor.
Aim:
To assess the immunogenicity in previously untreated patients (PUPs), a prospective clinical trial has been initiated in 2000. This included 48 PUPs with severe hemophilia A after treatment with octanate for an observational period of 100 exposure days and at least 6 months.
Methods:
Patients with severe haemophilia A without previous exposure to FVIII or FVIII containing products were enrolled. Efficacy and tolerability are assessed by a 4-point verbal rating scale. Inhibitor assay, according to modified Bethesda method is tested pre-treatment, every 3-4 exposure days (ED 1-20) and every 10 EDs (ED 21-100) but at minimum every three months.
Results:
Two of 48 (4.2%) subjects receiving treatment developed clinically relevant inhibitor titers over the course of the study. Another two displayed inhibitors that disappeared spontaneously without change of dose or dosing interval. All inhibitors developed under on- demand treatment and before ED 50. From the 48 subjects, 42 had exceeded 50 EDs at the time of this analysis. octanate was well-tolerated and the adverse event profile was consistent with the population studied. The haemostatic efficacy in prophylaxis and treatment of bleeding were generally rated as “excellent” and no complication was reported for any surgical treatment.
Conclusion:
Despite frequent inhibitor testing and predominant on-demand treatment, octanate showed a low rate of clinically relevant inhibitor formation (4.2%) in this cohort of patients.
Objective:
Safety and efficacy of long-lasting recombinant factor IX Fc fusion protein (rFIXFc), currently being developed to provide extended protection from bleeding in hemophilia B patients, were demonstrated in the phase 3 B-LONG study, where a half-life of 82 hours was observed. Here we describe how patients in B-LONG who were on prophylaxis with FIX prior to study entry were treated with rFIXFc and their clinical outcomes during B- LONG.
Methods:
Patients who were on prophylaxis with FIX prior to study entry were identified. Patients’ self-reported FIX dosing regimen and bleeding rates pre-study were compared to their rFIXFc dosing regimen and annualized bleeding rates on study. All patients were monitored for safety, including inhibitor formation.
Summary:
Of 123 patients enrolled, 48 received prophylaxis with FIX pre-study: 33 in Arm 1 (weekly prophylaxis: rFIXFc 50 IU/kg once weekly, dose adjusted based on FIX activity); 15 in Arm 2 (individualized dosing interval: rFIXFc 100 IU/kg every 10 days, interval adjusted based on FIX activity). The most common pre-study dosing intervals were twice weekly (67%), thrice weekly (18%), and once weekly (13%). The 21 patients in Arm 1 reporting twice weekly dosing pre-study had a median pre-study dose of 36.4 IU/kg per injection (total weekly dose: 72.7 IU/kg); in their last 3 months on-study, these patients received a median dose of 36.4 IU/kg rFIXFc once weekly. The 9 patients in Arm 2 reporting twice-weekly dosing pre-study had a median pre-study dose of 37.9 IU/kg per injection (total weekly dose: 75.9 IU/kg); in their last 3 months on-study, these patients received a median dose of 103 IU/kg rFIXFc at a median interval of once every 13.5 days. Overall, Arm 1 patients on prophylaxis pre-study reported a bleeding rate of 2.5 in the 12 months prior to study entry; on-study, they had an annualized bleeding rate of 2.1. Arm 2 patients on prophylaxis pre-study reported a bleeding rate of 2.0 in the 12 months prior to study entry; on-study they had an annualized bleeding rate of 0.0. Based on population pharmacokinetic modelling, approximately 95% of people with hemophilia B receiving 50 IU/kg rFIXFc once weekly were predicted to maintain FIX trough levels above 1% at all times. In the B-LONG study, rFIXFc was well tolerated and no inhibitor development was detected.
Conclusions:
Prophylaxis with rFIXFc may provide patients who are currently on prophylaxis the option for dosing every 1-2 weeks with low bleeding rates.
Objective:
Describe social worker and nurse perspectives on the Hemophilia Experiences, Results and Opportunities (HERO) results from Canada.
Methods:
Adults with hemophilia (“adults,” ≥18 years) and parents of children (<18 years) with hemophilia (“parents”) were recruited through local hemophilia organizations and completed an online psychosocial assessment. Advisory board meetings with Canadian social workers and nurses were held to discuss the HERO results in January and April 2013, respectively.
Summary:
Key psychosocial issues identified by social workers and nurses included issues with sex life, pain, and employment. One-half (9/18) of adults with hemophilia in Canada reported that hemophilia had affected the quality of their sex life. Social workers noted that there is a need for more discussions and professional support regarding sexual intimacy, in addition to a need for more training for healthcare professionals (HCPs) on how to engage in conversations about sexual intimacy. Possible solutions to this issue provided by nurses include handouts to start conversations, education on strategies for HCP seminars, websites with patient testimonials, and information nights through local hemophilia chapters. Overall, 9/30 adults with hemophilia reported that pain had interfered with their daily life extremely or quite a lot. Of 27 adults, 9 reported pain all the time and 13 reported pain all the time that gets worse when they have a bleed. Social workers noted that there is a lack of chronic pain care and there needs to be an increase in sensitivity toward pain issues. Solutions proposed by nurses included a literature review about pain-assessment tools for hemophilia, developing tools to teach parents how to assess pain, developing an application for assessing and managing hemophilia-specific pain, offering pain intervention, developing distraction tool kits, and teaching alternative ways to cope with pain. Only 15/29 Canadian adults with hemophilia were employed; 35/39 parents were employed. Social workers noted that there is discrimination at work and school. To improve career guidance, nurses suggested the following: explore vocational issues, increase hemophilia treatment center (HTC) awareness, capture facts around what is or is not possible with respect to jobs, vocational support programs to start earlier, and clarify the HTC’s role in advocacy.
Conclusions:
HERO provided key insights into psychosocial issues facing Canadian adults with hemophilia and Canadian parents of children with hemophilia. Nurses and social workers provided strategies that could help improve the lives of both patients and parents.
Objective:
Caregivers of hemophilia patients may experience physical, social, emotional and financial problems as a result of their care tasks. Measurement of the caregiver experience is important in hemophilia as the majority are informal caregivers; typically unpaid family or friends. In order to carry out studies within the United States, a need exists for a translated and validated instrument to measure informal caregivers’ care-related quality of life in English for the U.S.
Methods:
The CarerQol instrument, covering 7 domains measuring the care-related quality of life of informal caregivers, including fulfillment, relational, mental and physical health problems, social impact, receipt of family support and financial impact, was selected on which to base an English U.S. version. The Dutch (Netherlands) source was translated into English (U.S.) by two forward linguists, working independently, who then collaborated to create a harmonized version. The project team, consisting of the forward translators, project manager, survey research analyst and independent Dutch (Netherlands) reviewer, discussed the harmonized English (U.S.) version to make necessary revisions. The English (U.S.) harmonization was then back-translated into Dutch (Netherlands), and a second Dutch linguist compared the back-translation to the source Dutch to ensure conceptual equivalence of the English forward translation and Dutch source. A client representative, who is a native English (U.S.) speaker, reviewed the English translation against the Dutch as an additional quality measure. After the English (U.S.) harmonization was finalized, it was debriefed via telephone interviews with 5 volunteers using screenshots of the questionnaire’s web version.
Summary:
A total of 5 subjects from the U.S. participated in debriefing interviews. Subjects ranged in age from 24 to 59 years, with educational levels ranging from 11 to 16 years. Sixty percent (60%) of the sample was female. Interview data confirmed that the English (U.S.) harmonized translation is conceptually equivalent to the source Dutch, and is understood by subjects in the United States.
Conclusion:
Per the cognitive debriefing results, the English (U.S.) harmonized translation based on the Dutch CarerQol instrument adequately captures the concepts in the original Dutch and, overall, is easily understood and confirmed as culturally appropriate by subjects in the United States. The resulting instrument is validated for use by English speakers in the United States, and captures the 7 quality of life domains as included in the source instrument.

Objective:
Describe the role of H. pylori as a cause of chronic iron deficiency in children with congenital bleeding disorders.
Methods:
As part of their routine comprehensive care children at our haemophilia treatment center have a CBC done. Over the past year 4 children who underwent diagnostic workup for microcytic anemia were found to have iron deficiency associated with H. pylori infection. We describe the clinical findings in these children and their outcomes after appropriate therapy.
Summary:
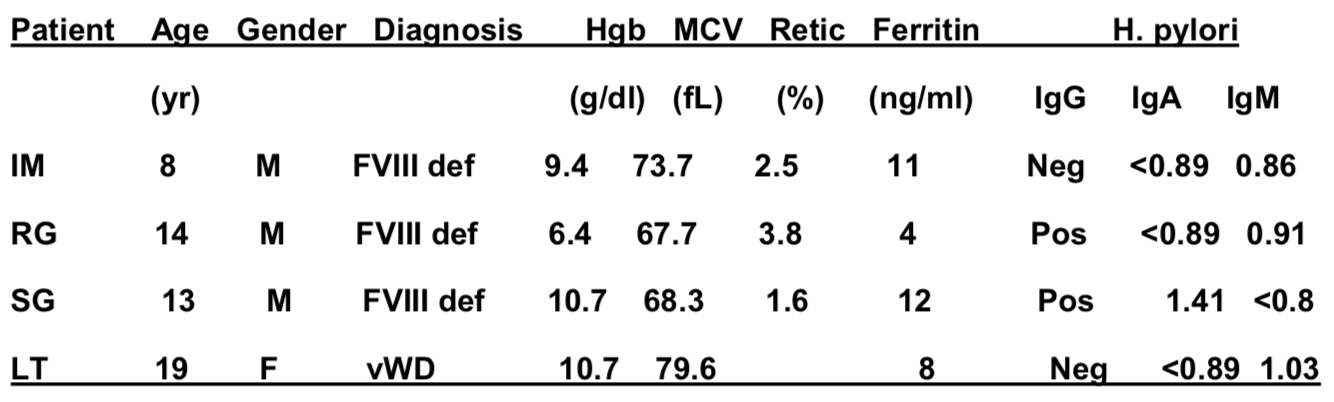
From March 2012 to March 2013, 4 children were identified with iron deficiency anemia due to H. pylori. None of the 4 patients gave a history of excessive blood loss and none had GI symptoms such as weight loss, abdominal pain, vomiting or diarrhea. Clinical and laboratory findings at presentation are summarized below. No patients had thrombocytopenia.
Only one patient had positive occult blood in stool (RG) and underwent endoscopy. Diagnosis of H. pylori was made on gastric biopsy. RG also had 4 weeks of IV iron sucrose therapy. All patients were seen by gastroenterology and successfully treated with triple therapy consisting of amoxicillin, Biaxin, and omeprazole. RG had a recurrence and was retreated with quadruple therapy consisting of amoxicillin, metronidazole, omeprazole, and bismuth subsalicylate. All 3 patients with FVIII deficiency were also on secondary prohylaxis.
Conclusions:
H. pylori is a common cause of gastritis and often presents with upper gastrointestinal symptoms. It is also associated with idiopathic thrombocytopenic purpura. However, in children with congenital bleeding disorders, it may present with few symptoms and an incidental finding of iron deficiency anemia. We suggest that children with bleeding disorders should be screened for H. pylori as a cause of iron deficiency.
This research project will examine fall history and fall risk in patients with hemophilia. Multiple risk factors for falls identified in the general population are prevalent in the hemophilia population. Existing data suggest that fall rates may be higher and that fall risk may begin at an earlier age in patients with hemophilia. Identification of fall risk enables early intervention, thereby preventing injury and fear of physical activity, both of which have been associated with falling and may carry an increased risk in patients with bleeding disorders.
Dr. Smith's research focuses on better understanding the development of factor VIII inhibitors. Specifically, she will focus on the effects of chemical signals, or cytokines, secreted by helper T cells on the development of inhibitor antibodies. She hypothesizes that certain cells, called Th17 cells, play an important role in the development of these antibodies by stimulating inflammation and driving the immune response toward inhibitor production. Dr. Smith received a BS from the University of Delaware before earning her Ph.D. from Montana State University. Prior to her appointment as an Assistant Professor at the University of Texas Medical School at Houston, she spent four years as a postdoctoral research fellow at the University of Michigan.
The objective of this study is to collect a large data base of gait parameters on individuals from the age of 12 months to 99 years old who do not have neuromotor deficits. This ongoing study will be the basis of comparison for people with hemophilia as a means to identify gait deficits that occur due to joint or muscle involvement from the bleeding disorder as compared to gender and age matched controls. We are using the GaitRite electronic walkway evaluation system as the quantitative measurement tool for gait analysis. Enrolled subjects are consented to this study and to the storage of data in a gait repository for future studies. This data will be available to other Hemophilia Treatment Centers upon written request to our Gait Repository Guardian (currently Dave Oleson, PT at the Hemophilia Treatment Center at CDRC in Portland, OR).
Menstrual cycles for females with bleeding disorders can present special challenges not experienced by other girls and women. Having your period can be physically, social and emotionally exhausting. A new web-based application is now available and can be downloaded to your personal mobile device or desktop computer. With this application you can track how long your period lasts, how much you are bleeding, any interventions utilized and how it is affecting your daily life. This is a new web-based application you can download that is free and available to all girls and women with bleeding disorders through their federally funded hemophilia treatment center (HTC).